

Author: 'Clinician's Survival Guide To The Chatbot Revolution' Professor & Chair Emeritus, Duke Dept of Psychiatry Chair, DSM-IV Task Force
Joined February 2013
- Tweets23K
- Following534
- Followers32.4K
- Likes2.8K





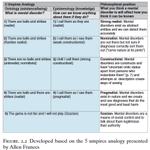
Great piece explaining current profusion of diagnostic fads & obstacles to corrective "de-diagnosis".
3 causes:
1)Demand led self-diagnosis rather than careful clinical evaluation 2)Identity-conferring rather than descriptive labeling 3)Self-reinforcing rather correctable

"Diagnostic revision may correct error; it may also threaten identity, access to support and self-understanding, fall unequally on particular groups, or become a mechanism for rationing" pubmed.ncbi.nlm.nih.gov/4292… From @DrMariosAdamou et al. De-diagnosis is a rising topic.

For 4000 years, Medicine/Psychiatry were based on superstition & placebo effect- most "treatments" worthless or toxic.
Past 100 years- scientific medicine with many proven treatments.
But superstition dies hard- "herbal supplements" are $250 billion industry.
Good debunking:

"Bravo! The wave of evidence for — and against — CAM treatments is distilled by one of my favorite voices in psychiatry."
— Drew Ramsey, MD
"And against" is the part that makes it useful. 67 treatments, 1,796 trials.
thecarlatreport.com/products…

Class action lawsuits are only effective way to tame the constant malpractice of big tech companies that are practicing without a license or regulation.
Has aleady worked re causing addiction & privacy invasion.
Could work re promoting fake diagnosis/psych disorders/suicide.

TikTok suggests there's something wrong with us, usually ADHD or autism, even when we don't ask, concludes this new investigation into the algorithm:
psych-partners.com/how-dr-ti…

50 yrs/$80 billion of
#Alzheimers research a collosal flop producing no diagnostic test/no effective treatment.
Now getting silly- pushing 19th century superstition head shape predicts destiny.
We must spend more on better care/less on fountain of youth. nytimes.com/2026/10/22/scien…

Most human clinicians are way too complacent about chatbots.
Don't realize most patients already use them between sessions.
Here's my advice re taming chatbots, turning them into useful assistants not harmful rivals.
Easy to do even for techno-idiot like me.
Good interview:

My latest expert interview with @AllenFrancesMD explores mental health chatbots, their potential benefits and risks, privacy, and the role of human therapists.
Read the full interview:
all-about-psychology.com/all…

4 thoughts re post partum disorders:
1)Crucial psychs get better training- but even more for Peds & Ob/Gyn MDs & nurses
2)Single screening not enough-must be every visit 3)4 week criterion is arbitrary-screen symptoms for 3 months
4)Way under-researched
Read this useful review:
Yes, and to screen for postpartum psychosis, here are some instruments
psych-partners.com/why-postp…

Brilliantly explains the awful process by which social media tricks the worried well into believing they're mentally ill.
Should be read by everyone tempted to self diagnose psych disorders.
Here’s how TikTok convinces people they have mental illness without any prompting from the user:
psych-partners.com/how-dr-ti…

Stages in mad rush to psych overdiagnosis:
1)DSM-III sells millions of copies making psych dx a cultural phenomenon
2)Big Pharma sells ills to peddle pills
3)Careless clinicians diagnose patients they barely know
4)Massive & usually wrong internet self-diagnosis
Useful survey:

It's time to talk about mental health, medicalisation, and overdiagnosis.
When polls show that people think autism, ADHD, and anxiety are overdiagnosed, a common reply is:
"The public don't know what they're talking about. Ask an expert."
So that's exactly what I did. And it turns out experts are far more concerned than the public!

I am usually against psych screening because it creates vast #s of false positives/stigma/wasted resources.
But psych screening should be universal pre & post partum.
True positive rates are high & psych disorders put both mother & baby at risk, as well as their bonding.

Many research studies have shown that untreated depression during pregnancy adversely impacts the mental health of the child as well as the mother. ow.ly/R4wK50ZZ4oE

Allen Frances retweeted
Road to hell is paved with good intentions & bad unintended consequences.
We included Bipolar-II in DSM-IV to reduce risk of antidepressants causing mania/rapid cycling in people with bipolar risk.
But Pharma promoted massive over-diagnosis & overuse of harmful antipsychotics.
This Post is from an account that no longer exists. Learn more
Allen Frances retweeted
Biggest DSM IV error was adding Bipolar 2:
Pushed by Pharma & over-diagnosed by MD's, it led to harmful/unneeded use of antipsychotic meds. xitter.cf/TheBJPsych/status/8578… – at California, USA

Hypomanic symptoms might identify those at greatest risk of developing bipolar disorder bit.ly/2p7paP2 @UofT_dlsph @rcpsych

Allen Frances retweeted
Serious suggestion to improve psychiatric training & care:
All training programs & large scale providers should be required to run a lithium clinic for bipolar disorder & clozapine clinic for schizophrenia.
Not having these= neglecting the severely ill/treatment non-responders.

In AI world, we need to radically change who gets into medical school.
All medical info is now readily available, but great clinical judgment is rare & the human touch is almost lost.
Being book smart is now much less important than having common sense & being people smart.

Medical students admitted solely by grade point average show a narrow but highly prosocial personality profile
link.springer.com/article/10… via @jarlebreivik et al

Allen Frances retweeted
Human emotional distress is ubiquitous. Psychiatric disorder is pretty rare. Conflating them causes big trouble.
30 yrs ago, wild fad psych diagnosis was promoted by Big Pharma/mostly done by the MDs.
Internet is now to blame & the loose self labelling is done by the patients.

When a Diagnosis Becomes Just a Word: The Problem of Popularized Mental Health Words versus Professional Diagnoses.
Psychiatric diagnoses are unusually vulnerable to popularization and misuse. Most people don’t casually diagnose each other with liver disease or orthopedic disorders. But mental-health concepts describe experiences woven into everyday life—mood, attention, personality, relationships, behavior. That familiarity creates an illusion of expertise. A carefully defined clinical construct becomes a familiar word, and the word gradually gets mistaken for the construct itself.
People with severe mental illness usually need meds- but always also need #psychotherapy & social work help.
But few therapists train in this work/few patients have insurance.
Beck's "Recovery-Oriented Cognitive Therapy for Serious Mental Health Conditions" is best solution.

🧠 Evidence-based psychosis-specific psychotherapies are recommended across the schizophrenia spectrum. However, training in these specialized therapies is often not mandatory for psychotherapists, leading to a fragmented field of expertise.
This large-scale survey of 1,382 psychiatrists and clinical psychologists in Switzerland assessed self-reported psychotherapy workshop attendance for psychosis. Nearly half of participants attended at least one workshop, although only roughly a third had attended as part of their mandatory psychotherapy training.
🔎 Social network analyses revealed that the overall psychosis psychotherapy training landscape remains highly fragmented and without clear training pathways. Popular workshops included cognitive behavioral therapy for psychosis and psychoeducation, but co-attendance rates between different workshop types rarely exceeded 10%.
Furthermore, attendance patterns differed significantly based on occupational roles (psychiatrists vs. psychotherapists) and therapeutic orientations (CBT vs. psychodynamic vs. systemic vs. humanistic), indicating inconsistencies in access.
💡 These findings highlight the urgent need for evidence-informed measures to address training gaps and promote guideline-aligned specialization pathways.
🔗 Read the full study:
nature.com/articles/s41537-0…
#CBT #MentalHealth #Psychosis #PsychotherapyResearch
If you consciously set out to develop the world's worst possible mental health non-system, you would come up with the absolute mess we have created in the US.
The barriers that patients face when trying to access mental health care are numerous, including extensive wait times, limited in-network options, and ghost networks—in which insurance directories are padded with clinicians who can’t or don’t actually provide care. alert.psychnews.org/few-call…

Cruel paradox:
We over-diagnose/over-treat worried well while neglecting the really sick.
Awful misallocation of resources started in 1980 with 2 unrelated events: 1)DSM-III
2)Community mental health centers defunded
If all are "sick", desperate needs of really sick go unmet.

"Normal human emotions are being diagnosed as disorders, according to mental health experts.
More than four in five mental health professionals believe that normal thoughts are being 'medicalised', with anxiety, depression, autism – and attention deficit hyperactivity disorder (ADHD) in particular – being overdiagnosed, according to a survey.
The majority of practitioners also think mental disorders are being 'glamourised' and that having a neurodevelopmental condition has become a desirable personality trait."
buff.ly/K014YiY

Reagan definitely had terrible intentions when he stopped federal funding of community mental health centers.
& no powerful political leader since has cared enough to correct the criminalization of mental illness/support adequate community care/or correct shortage of housing.

Reagan played his part but he was one player acting in one act in what looks to me like a four act tragedy. Critical steps occurred before and after his federal career. No one had bad intentions. No one with the power to make decisions understood the consequences of their decisions.
My own take is that as asking for government money became more and more an economic foundation and socially acceptable to people in all ranks of society, the traditional acceptable objects, the weakest least able to care for themselves, got trampled in the dust.
Too many pigs, not enough tits. The weak piglet gets shoved out. In human terms it is the people who don't vote, can't work the system, can't make themselves into a cohesive political force who are shoved aside.
Reagan destroyed care for people with severe mental illness by privatizing it.
Private systems care only about profit & cherry pick the easiest patients.
Result: People who really need treatment can't get it & wind up homeless or in jail.

Why do private psychiatric hospitals turn away complex patients?
A new psychiatric hospital opens, and families think, “Maybe now there will be help.”
But what if your loved one needs constant supervision? What if they have a medical condition that requires extra nursing care? Dr. Carol Olson explains why more beds don’t necessarily mean more access for the people who are most ill.
Then where do they go? That’s the question I can’t leave alone.
In Episode 3 of Mama Bear Diaries, we talk about who our system can serve, who it struggles to serve, and what it would take to close those gaps.
Allen Frances retweeted

Why do private psychiatric hospitals turn away complex patients?
A new psychiatric hospital opens, and families think, “Maybe now there will be help.”
But what if your loved one needs constant supervision? What if they have a medical condition that requires extra nursing care? Dr. Carol Olson explains why more beds don’t necessarily mean more access for the people who are most ill.
Then where do they go? That’s the question I can’t leave alone.
In Episode 3 of Mama Bear Diaries, we talk about who our system can serve, who it struggles to serve, and what it would take to close those gaps.