





Geoff retweeted

Please stream this video my wife & I had a small part in producing. 40 min about the invasion of Minneapolis by ICE, brutalizing people of color & the neighbors trying to help & protect them. $10.00 to help make it successful. Offline Sat 10/24!
twincitiesfilmfest.org/film-…
Geoff retweeted
this is a super important podcast, you should all listen to this now.
I will have some additional thoughts on this topic in a few days, but for now your assignment is to read this post and listen to the podcast. #SpacedRepetition

EMCrit 436 - When you RSI Shocked Patients, they Tend to Die
8 years later, we are bringing HNI out of the expert-only realm so anyone can intubate shocky patients safely without causing post-intubation arrest & hopefully not causing any BP/CO drop at all...
[#FOAMed for Now]
emcrit.org/436

Geoff retweeted

I used @claudeai to build an interactive tool called AngioView (angioview.com) to help you understand coronary angiograms.
One of the most challenging parts of being a first-year cardiology fellow is learning how to interpret cath lab imaging.
It can take a lot of repetition before you're able to create a mental 3D map of coronary anatomy, which is so important because you need to understand how changes in cranial/caudal and LAO/RAO angulation affect the overall coronary perspective.
I never found a high-quality tool out there to help visualize all this (at least not for free) so hopefully this site helps speed up that learning process!
Geoff retweeted

EMCrit 436 - When you RSI Shocked Patients, they Tend to Die
8 years later, we are bringing HNI out of the expert-only realm so anyone can intubate shocky patients safely without causing post-intubation arrest & hopefully not causing any BP/CO drop at all...
[#FOAMed for Now]
emcrit.org/436
Geoff retweeted
Updated the chapter on extubation 😁
Determining whether the patient "passes" an SBT is perhaps the biggest clinical conundrum.
Rapid-Shallow Breathing Index (RSBI) is commonly used to gauge whether the patient passes an SBT. However, this is only moderately predictive of the ability to extubate:
👍 RSBI <105 indicates +2 likelihood ratio of successful extubation
👎 RSBI >105 indicates a 0.3 likelihood ratio of successful extubation
RSBI <105 doesn't guarantee success, because it only measures if the patient is strong enough to breathe (the patient may still fail to clear secretions or maintain their airway).
RSBI >105 doesn't guarantee failure. Especially in the context of chronic respiratory dysfunction (COPD, ILD), patients may still be extubatable (especially extubation of COPD patients directly to BiPAP).
Ultimately, there's no easy answer. Clinical judgement and experience are needed. Vibes. Often you need to repeat the SBT and see exactly what happens and how the patient "failed."
There is only ONE test with 100% sensitivity and specificity for the ability to extubate: removing the endotracheal tube and seeing what happens. Patients continue to surprise me and remind me that we cannot foresee the future, so sometimes we need to just empirically try.
The main improvement to the chapter is better organization with quick links to commonly encountered problems.
(#1/2, link in next post)
#AlwaysBeExtubating

Geoff retweeted

I appreciate this unsolicited swipe at Canadian ERs. But guess what happens when you call a cardiologist about a low positive troponin at 0400AM? Sure, go ahead and blame ER - everyone does. But first understand what ER faces to get cardiology interest in a case. 👇👇👇
It could be true that the threshold of a high sensitivity troponin for diagnosing myocardial ischemia in women is different. If that's new - which it would be - that's important.
Professional guidelines and continuing education has not reflected this possibility. In the last 2 weeks, I attended 2 lectures by physicians passionate about diagnosing myocardial infarction and there was zero mention of the concerns raised in this article. It could be charged that is the problem - doctors are dumb and sexist - but again, these are physicians with an incredible research, publishing and teaching record in diagnosing MI in all types of patients. They are dedicated to finding the elusive heart attacks.
New guidelines could be forthcoming but that doesn't excuse taking a swipe at ERs that are doing their best under difficult circumstances. Avis should take a breath and talk to an ER doctor next time before unloading a headline on ER.
When you call cardiology about a female with a low troponin - they'll account for it over the phone, calling it "strain" or not worrisome and direct you to outpatient follow-up or calling internal medicine. You can call a cardiologist about a patient with EKG changes, worrisome troponin, and active chest pain, and they are not going to rush in every time. That's reality.
Would ER like more cardiology interest? Sure. Just remember, it's cardiology and not ER that control who gets interventional angiography.
ER behaves the way it does because it knows the interest of cardiology. They know the institutional guidelines when to call them. ER isn't making the rules, they are following them.
This article does cite important anginal equivalents like nausea, shortness of breath and indigestion - and in defense of ER - this is well known. If you ask a real ER doctor - we are smashed by EKGs for far far less during a regular shift. These types of patients are already being evaluated for myocardial ischemia. But too bad Avis didn't think of asking an ER doctor what happens in the ER rather than just taking a kick at them and the brutal work they do when everyone else is having Thanksgiving turkey.
Favaro cites Alberta data saying "300 women a year were sent home from emergency departments in the province, then returned with a heart attack within 30 days". No where in the article (which I read) does it actually describe what really happened. Was it because the ER doctor made a mistake? Was it because cardiology refused to see the patient despite the advocacy of the ER doctor? Was it because the hospital guidelines meant the patient was ineligible for real-time cardiology consultation? We don't know. The articles doesn't say. But yah, it's all ER's fault as the click-bait headline reads.
ER is an easy target for criticism. But very few can do the job for a career. And if you do, you should be ready for criticism by people on the sidelines who aren't going to put on a stethoscope and see patients. This type of journalism - isn't helping the situation. It's click-bait and riles up people to read the article and learn how they've been shafted by dumb and uncaring doctors and to be upset at ER when ER is powerless over who gets invasive testing.
So - to conclude - would ER like more cardiology interest in women - yes, for sure. But maybe blame the cardiologists alongside the ERs because at 0400AM we know who is working hard in terrible conditions getting the middle finger from patients, getting kicked punched and swore at - and who isn't. @Avis_Favaro @ECGcases @smithECGBlog @amalmattu

Geoff retweeted
I’ve always said the worst thing you can be if you have a myocardial infarction is a young woman. And most of the problem is with cardiologists, not EM. Everyone should be using the.@PMcardioApp queen of hearts, AI ECG model to avoid these mistakes.
drsmithsecgblog.com/tag/youn…


I appreciate this unsolicited swipe at Canadian ERs. But guess what happens when you call a cardiologist about a low positive troponin at 0400AM? Sure, go ahead and blame ER - everyone does. But first understand what ER faces to get cardiology interest in a case. 👇👇👇
It could be true that the threshold of a high sensitivity troponin for diagnosing myocardial ischemia in women is different. If that's new - which it would be - that's important.
Professional guidelines and continuing education has not reflected this possibility. In the last 2 weeks, I attended 2 lectures by physicians passionate about diagnosing myocardial infarction and there was zero mention of the concerns raised in this article. It could be charged that is the problem - doctors are dumb and sexist - but again, these are physicians with an incredible research, publishing and teaching record in diagnosing MI in all types of patients. They are dedicated to finding the elusive heart attacks.
New guidelines could be forthcoming but that doesn't excuse taking a swipe at ERs that are doing their best under difficult circumstances. Avis should take a breath and talk to an ER doctor next time before unloading a headline on ER.
When you call cardiology about a female with a low troponin - they'll account for it over the phone, calling it "strain" or not worrisome and direct you to outpatient follow-up or calling internal medicine. You can call a cardiologist about a patient with EKG changes, worrisome troponin, and active chest pain, and they are not going to rush in every time. That's reality.
Would ER like more cardiology interest? Sure. Just remember, it's cardiology and not ER that control who gets interventional angiography.
ER behaves the way it does because it knows the interest of cardiology. They know the institutional guidelines when to call them. ER isn't making the rules, they are following them.
This article does cite important anginal equivalents like nausea, shortness of breath and indigestion - and in defense of ER - this is well known. If you ask a real ER doctor - we are smashed by EKGs for far far less during a regular shift. These types of patients are already being evaluated for myocardial ischemia. But too bad Avis didn't think of asking an ER doctor what happens in the ER rather than just taking a kick at them and the brutal work they do when everyone else is having Thanksgiving turkey.
Favaro cites Alberta data saying "300 women a year were sent home from emergency departments in the province, then returned with a heart attack within 30 days". No where in the article (which I read) does it actually describe what really happened. Was it because the ER doctor made a mistake? Was it because cardiology refused to see the patient despite the advocacy of the ER doctor? Was it because the hospital guidelines meant the patient was ineligible for real-time cardiology consultation? We don't know. The articles doesn't say. But yah, it's all ER's fault as the click-bait headline reads.
ER is an easy target for criticism. But very few can do the job for a career. And if you do, you should be ready for criticism by people on the sidelines who aren't going to put on a stethoscope and see patients. This type of journalism - isn't helping the situation. It's click-bait and riles up people to read the article and learn how they've been shafted by dumb and uncaring doctors and to be upset at ER when ER is powerless over who gets invasive testing.
So - to conclude - would ER like more cardiology interest in women - yes, for sure. But maybe blame the cardiologists alongside the ERs because at 0400AM we know who is working hard in terrible conditions getting the middle finger from patients, getting kicked punched and swore at - and who isn't. @Avis_Favaro @ECGcases @smithECGBlog @amalmattu
Geoff retweeted

Queen of Hearts’ FDA approval was the #1 most-read story in September on TCTMD, one of the leading interventional cardiology resources!


Geoff retweeted
50-year old with chest pain: serial ECG ‘STEMI negative:’ does the patient have Occlusion MI (OMI)?
drsmithsecgblog.com/50-year-…
Highlights the stupidity of the NSTEMI guidelines: "NSTEMI" is worthless, and no one follows the "high risk" NSTEMI guidelines.
@ECGcases @PMcardioApp

Geoff retweeted

Something an EP attending taught me in fellowship that has stuck with me: If someone has permanent Afib, Afib with rapid rate is their "sinus tachycardia".
Anything that would cause sinus tachycardia in someone without Afib (infection, stress, dehydration, etc), would cause "AF RVR" in a person with Afib. It is not a new de novo condition for them.
Stop chasing the AF RVR, treat underlying condition, the RVR resolves on its own.
#cardiology #EP #Afib
Geoff retweeted
The central theorem of RV failure 😁
In LV failure, excessive afterload reduction can cause systemic hypotension (MAP << 60mm), vasodilatory shock, systemic malperfusion, and death.
In RV failure, excessive afterload reduction doesn't really exist. Low pulmonary artery pressures are well tolerated (the lung remains well perfused by *dual* pulmonary & bronchial artery circulations).
This essential difference opens a unique avenue for treating RV failure with much more aggressive afterload reduction (as compared to LV failure).
The RV is different from the LV and requires unique management strategies (not just copy/pasting a generic LV failure strategy).
#ThePeoplesVentricle

Geoff retweeted
whoever decided to define everything in terms of the *overlapping* terminology of "myocardial infarction" (MI) and "myocardial injury" (also MI) needs to go straight to jail.
this gives birth to amazing phrasology like "acute myocardial injury not due to myocardial infarction."

NEW 2026 #ESCGuidelines - Fifth Universal Definition of Myocardial Infarction (2026) 👇
ow.ly/yn8J50ZGofb
#ESCCongress

Geoff retweeted
in response to this blog, lots of folks commented that hyperangulated videolaryngoscopy is great at visualizing the cords but makes tube passage difficult
my team hasn't encountered this problem. why??
I think it's because we use sniffing position +/- laryngeal manipulation


Fresh Blog: Why I think hyperangulated videolarygnoscopy should be the mainstay of ICU intubations:
📹 People actually use the tool correctly
📹 Master one technique for easy & hard airways
📹 Compatible with steep bed angulation
📹 The fresh COVALENT RCT 😁
(#1/2)

Geoff retweeted

QOH gets it right. Steve, I, and Dr Sgarbossa have for years tried to educate people on this, and I know for many it will help them see it on their own. This unbiased AI ECG (blinded to all pt info except the ECG) shows that it can be done!

Geoff retweeted
I’m so exhausted with this BS about piptazo being nephrotoxic.
I’ve written blogs on this since 2016
There was never a plausible mechanism for nephrotoxicity
The ACORN RCT validated this
Great example of academics publishing bad studies that cause harm
Please stop. #1/2

Geoff retweeted

Sepsis + AKI + bradycardia + home beta blocker or CCB = BRASH syndrome.
Anand Swaminathan, MD (@emswami) from ResusX:ReUnion:
This isn't an OD — their kidneys just stopped clearing the drug. Standard pressors won't work. What's your next move at the bedside? Comment below.👇
Geoff retweeted
SOHO trial in NEJM:
🏙️ Multicenter RCT comparing high-flow nasal cannula vs. low-flow oxygen among patients with acute hypoxemic respiratory failure (mostly pneumonia)
🏙️ Inclusion criteria required a respiratory rate >25 and substantial hypoxemia (P/F <200)
🏙️ No difference in the primary endpoint of mortality (not surprising, the mortality endpoint is nearly always neutral in modern RCTs evaluating the nuances of supportive care).
🏙️ HFNC reduced the rate of intubation and increased the number of ventilator-free days.
🏙️ No significant signals of harm from HFNC.
This is similar to the FLORALI trial (by the same group of investigators). However, FLORALI showed *improvement* in mortality, whereas the current study didn't.
Why do these studies disagree about mortality?
The FLORALI trial found no mortality difference between HFNC versus conventional oxygen among ALL PATIENTS. However, it DID find a mortality difference in the *subgroup* of patients with P/F <200.
So this is a classic tale in critical care - a subgroup analysis from one trial subsequently fails to replicate. (At least, in terms of the mortality benefit.)
But chasing mortality in these trials is a fool's errand. Overall, the SOHO trial still supports the use of HFNC in acute hypoxemic respiratory failure (in terms of reduced intubation and improved ventilator-free days).
Using HFNC for sick pneumonia patients is already standard care, so I don't see this changing practice very much. Keep calm and HFNC on. 🌬️

For patients with acute hypoxemic respiratory failure, whether high-flow oxygen is superior to standard oxygen in reducing mortality is unclear. Research findings from the SOHO trial are summarized in a new Quick Take video. nej.md/4x706JY
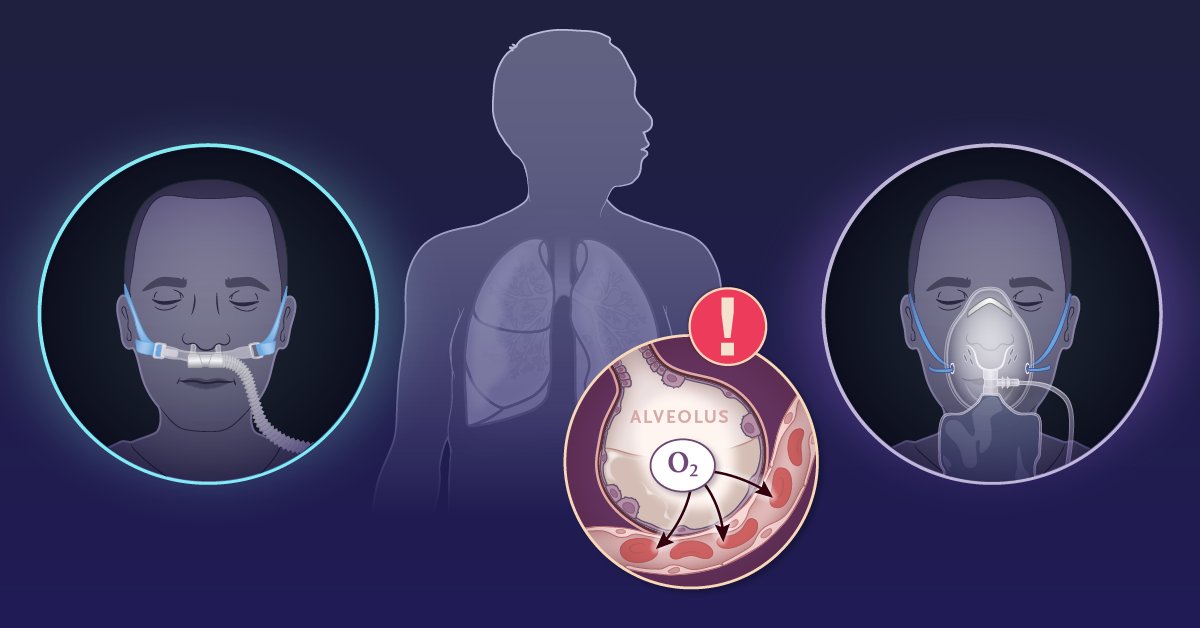
ALT An illustration showing a patient receiving oxygen through nasal cannula on the left and standard oxygen on the right. In the center, there is a diagram highlighting acute hypoxemic respiratory failure with an oxygen (O2) symbol and an exclamation mark, positioned against a silhouette of lungs.
Geoff retweeted
Valproic acid is great for refractory agitated delirium.
🏆 Especially useful in patients with explosive/aggressive behavior in the context of a personality disorder (often exacerbated by delirium).
Candidates for VPA:
✅ Not pregnant
✅ No severe liver dz or history of hyperammonemia
✅ No major drug-drug interactions with VPA
✅ Didn't respond to antipsychotics +/- alpha-2 agonists (dexmedetomidine). This isn't a hard requirement, but generally VPA isn't usually a front-line agent.
Advantages of VPA:
👍 Cardiovascular stability
👍 Low risk of airway compromise (only mildly sedating)
👍 Antiseizure activity (e.g., can be used for sz prophylaxis in an agitated patient)
👍 Can be given IV or PO (1:1 conversion with immediate-release formulations)
👍 EM/ICU folks should be knowledgable and comfortable within it already
Disadvantages of VPA:
👎 Dosing requires a little more thought than most agents. For patients on this for more than a few days you want to check a VPA trough and adjust it using the Fraser equation (to account for albumin).
👎 Can cause a lot of side-effects (but most of these are due to *chronic* VPA, rather than just a few days of therapy)
Dosing
🎯 My preference is to use the same dosing regimen as for status epilepticus (40 mg/kg load max 3 grams, then 15 mg/kg/day in divided doses). You can up-titrate as needed while following VPA troughs if ineffective (max dose of 45 mg/kg/day).
🎯 Many studies have reported starting lower and up-titrating, but this delays its efficacy for 2-3 days.
🎯 Using more frequent doses (e.g., q6hr rather than q8hr) may avoid toxic peak levels while maintaining adequate trough levels.
This isn't an option I use a ton, but it's a terrific tool to have in your toolbox for agitated delirium that isn't responding to usual front-line treatments.
⚠️ VPA should be weaned off prior to hospital discharge (unless the patient is seen by psychiatry and they are intentionally recommending VPA as chronic outpatient therapy for bipolar disorder etc - which would be uncommon).
(more discussion on VPA pharmacology in the IBCC chapter on status epilepticus)
Recent article on this in NeuroCritical care here:

Thomas et al: Valproic acid for the management of agitation in neurosurgical intensive care unit patients
Link: link.springer.com/article/10…
@neurocritical #neurocritcare

Geoff retweeted
Proposal: for complex patients (eg ICU) we should *always* get CBC w/ differential (not plain CBC)
- Same amount of blood
- Run by the same machine (it usually CHECKS the differential & just dumps the data!)
- Trivial cost difference
- Can be helpful (eg Eos 2/2 drug, NLR)
