

Become a better endoscopist with EndoCollab, the world's most comprehensive endoscopy community. Join us: https://xitter.cf/t.co/EkRtunpQyB
🌎
Joined February 2021
- Tweets10.2K
- Following2.9K
- Followers31.2K
- Likes21.2K




EndoCollab™ | GI Endoscopy Community retweeted

Common misconception: APC only causes superficial damage.
Per the authors, persistent APC on one spot can cause carbonization, deep tissue injury, even perforation. Apply it dynamically.
By Adil Mir, MD, Reid Wasserman, DO and Klaus Mönkemüller, MD, PhD
EndoCollab™ | GI Endoscopy Community retweeted
Ischemic colitis: rectal sparing, segmental left colon disease, and a linear ulcer on the mesenteric border (Zuckerman's sign). Case by Klaus Mönkemüller, MD, PhD.


EndoCollab™ | GI Endoscopy Community retweeted
Extensive esophageal necrosis 6 hours after sodium hydroxide ingestion. Scope stopped at the EGJ because of perforation risk. Case by Klaus Mönkemüller, MD, PhD.


EndoCollab™ | GI Endoscopy Community retweeted
Barrett's with varices.
50-year-old patient sent for Barrett's esophagus and esophageal varices.
Band ligation of the Barrett's segment obliterates the varices and eradicates the Barrett's mucosa.
Case by Hiral Patel, MD and Klaus Mönkemüller, MD, PhD.


EndoCollab™ | GI Endoscopy Community retweeted
Cirrhosis, hematemesis and melena for one day. EGD shows this varix.
Which sign is it?
A) Red spots
B) Red wale sign
C) Nipple sign
D) Active bleeding
The case, and why the authors banded quickly, by Rami Musallam, MD and Klaus Mönkemüller, MD, PhD:
EndoCollab™ | GI Endoscopy Community retweeted
The snare keeps slipping off a flat lesion.
Pre-cutting EMR (hybrid ESD-EMR) in 3 steps:
1. Inject a submucosal cushion
2. Incise around the lesion with the snare tip (usually 1-2 mm exposure)
3. Snare in the groove and resect
Full technique by Klaus Mönkemüller, MD, PhD:
EndoCollab™ | GI Endoscopy Community retweeted
Find the bleeding source.
Duodenum case: recurrent overt GI bleeding, and two previous EGDs without significant findings. On the third look: active bleeding, no ulceration or angiodysplasia. Hemostasis with a through-the-scope clip.
Full case by Klaus Mönkemüller, MD, PhD:
EndoCollab™ | GI Endoscopy Community retweeted
A careful gastric examination is essential even when the indication is reflux.
Any focal change in contour, color, or surface texture deserves closer examination.


EndoCollab™ | GI Endoscopy Community retweeted
Guess the diagnosis: esophagus case with cottage-cheese plaques.
68yo with diabetes, dysphagia for 1 week. What do you see?
Drop your guess below, then see the full case (EGD + brushings + treatment):
thepracticingendoscopist.com…
By Klaus Mönkemüller, MD, PhD.
EndoCollab™ | GI Endoscopy Community retweeted
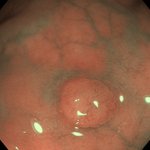
A 2 cm gastric lesion, found on an EGD for reflux.
Neither a bland color nor a smoothly lobulated contour reliably establishes the benign nature of the lesion.


EndoCollab™ | GI Endoscopy Community retweeted
Pedunculated polyp: clip the stalk before you snare?
The authors' preferred approach: hemostasis first. In this case, two clips, then hot snare above.
By Diana L. Dougherty, MD, MPH, and Klaus Mönkemüller, MD, PhD.
thepracticingendoscopist.com…
EndoCollab™ | GI Endoscopy Community retweeted
Patient on Eliquis. Large pedunculated polyp. There is always a feeding vessel in the stalk.
Clip the stalk, then snare.
Case by Klaus Mönkemüller, MD, PhD. AI-narrated.
thepracticingendoscopist.com…
EndoCollab™ | GI Endoscopy Community retweeted
No coils, no hemostatic powder, no over-the-scope clip.
So no endoscopic closure.
A transcatheter coil pack occluded the portal vein pseudoaneurysm.
Follow-up CT: complete resolution.

EndoCollab™ | GI Endoscopy Community retweeted
The orifice was a portal vein-duodenal fistula.
A portal vein pseudoaneurysm had ruptured into the bulb.
Endoscopy found the hole.
CT confirmed the pseudoaneurysm.


EndoCollab™ | GI Endoscopy Community retweeted
Large gastric ulcers after Y-90 radioembolization.
Fundus and proximal body.
Fibrin on the base, two visible vessels, and no active bleeding.

EndoCollab™ | GI Endoscopy Community retweeted
57-year-old man, massive hematemesis.
Lap cholecystectomy, then laparotomy for perforated appendicitis 10 days later.
After clot evacuation, this orifice sat in the duodenal bulb.
What is it?
Reply with your answer.

EndoCollab™ | GI Endoscopy Community retweeted
60-year-old man on Eliquis, stopped 2 days before colonoscopy.
Large pedunculated polyp in the sigmoid colon.
How would you resect it?
10 options in the last image.
Reply with your letter.


EndoCollab™ | GI Endoscopy Community retweeted
Plummer-Vinson syndrome on one sheet: the triad, the dilation, and why surveillance is lifelong.
Upper esophageal stenosis in a 78-year-old woman with chronic iron deficiency anemia.

EndoCollab™ | GI Endoscopy Community retweeted
Smooth extrinsic pinch of the bile duct.
No stone in the lumen.
This is pseudo-Mirizzi.
Surgery found an obliterated Calot triangle.


