

"Retarditas certa est."
Joined September 2025
- Tweets4.3K
- Following109
- Followers388
- Likes2.7K







$KLRA ceo talking doo doo on $VKTX and $pfe and others for these stupid varied dosing schemes 😂 "not a good use of our financial resources to prove what people can figure out for themselves." I said this previously, I like this CEO because he seems to focus on what matters. Just prove the thing is safe and effective and get it on the market. If someone wants to dose q2w or qm or standing on their heads in the shower, whatever, they will figure that out for themselves.
I do think vk2735 is a better molecule but ribu is a good molecule and vk CEO is frustrating because he talks too much about this dumb stuff that isn't what they should be focusing on to deliver value for shareholders.


Corollary to this imo it's a yellow flag when mgmt spends too much time and resources highlighting different dosing regimens etc (and that includes $VKTX stupid design of upcoming maint trial, as well as $pfe with their stupid monthly dosing gimmick). Focus on developing the best molecule and pricing it competitively and patients and practitioners will figure out how best to dose it in the real world.
1
11
2,391
Occam’s R̶e̶t̶a̶r̶d̶ Highly Regarded Allocator of retweeted
wtf, a rogue AI hacked my account and said this right at the low. Private discord bought 0dte calls and flipped them for big $$$$


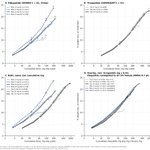
$KLRA Gemini-1 published so I could generate the cumulative dose-response curves. It looks a lot like tzp. 6mg should sit right on top of 15 mg tzp at 72 weeks if the male:female ratio was matched (G-1 was 54% F vs Surmount-1 68% F, which should make roughly a 1 pp difference). The sm-1 pbo group also ran 1pp ahead of g-1.
The separate 8 mg curve is smaller n = 49 and comparable Female % to typical western obesity trials.


$KLRA $LLY I've been looking more at placebo AE rates in glp-1 trials as a check on reporting standards. Looking at this ribupatide compared to Lilly's asian tzp trials. This is adjusted per patient year.
I know there's concern the results won't translate to a global population but when I look at the trends and think about how AEs and wl skew when going from asia to global, imo if anything they should be better in a global pop. All three terms (n,v,d) ran high in the ribu china placebo arm vs tzp asian trials and global pooled. I made some charts and tables to compare.
One thing, I hadn't realized previously that surmount-1 had really low rates of AEs compared to the later Surmount trials. The later trials are more consistent with each other. So if anything those are better bars for future glp/gips.


232
Dan you dumped your shi*coin $orbs or whatever it's called on all your retail followers right at the height of the stupid "crypto holding Co" bubble last year. You're a criminal. Same thing with your buddy Tom Lee and his ETH shitco.

No one individual can replace Jensen as CEO….but at the end of the day after this global scandal the old Jensen with the black leather jacket and rock star persona is gone for good….that cannot be replicated and any talk of a damaged Jensen coming back to Nvidia is ridiculous in our view given the legal/Board/DC scrutiny/moral compass/China tentacles. We see no chance Jensen comes back to Nvidia as CEO. It’s about moving forward for Nvidia and it starts Tuesday with earnings as Colette leads NVDA ahead (for now)
1
183
$LLY people were surprised at the AE rates from the eloraTZP data shared several weeks ago. It turns out the entire trial ran high on AEs compared to typical reporting patterns for similar trials in diabetics (using placebo and 15 mg tzp mono rates as a check). Also $NVO is not reporting any asthenia in some of their cagrisema t2d trials?


5
803
$NVO Cagrisema Redefine 9 AEs overall incredibly bad LOL no wonder they were hiding it. I included the terms from Redefine 1 as well for reference. So 1/1 and 1.7/1.7 both much WORSE than we saw in redefine 1 hence why they didn't brag about tolerability

$NVO still being tight-lipped on AEs from Redefine 9 (locked behind hard to access lancet D&E til clinical key updates) but at least now we know EE and TRE reverse between the 1/1 and 1.7 doses, consistent with no improvement in tolerability at the lower dose and actual observed worse tolerability at 1/1 in this particular instance.
Direct quote from my below post:
"On AEs and tolerability with CS, my guess they might not have seen much if any improvemen when reducing from 2.4 to 1.0, which is a general trend with amylins, and explains why they haven't shown an AE table, because if there were an improvement it would be something to brag about. In redefine 1 only <60% of those assigned to 2.4/2.4 finished on it, but those who stepped back down are pretty uniformly distributed across the lower doses, which also hints at no monotonic improvement in tolerability unlike how you see with sema 2.4."
5
6
1,799

Honestly I don't think monthly dosing matters and the long t1/2 could even be a liability $MBX. Convenience is increasingly a talking point for otherwise undifferentiated assets when you already have an extremely convenient once weekly injection. But it's weird they said they were going as high as 120 mg qm and in an interview they gave a pretty low bar for what they considered to be competitive weight loss.
So it will be interesting to see.

$MBX: JPMorgan - Upcoming 12-week multiple-dose data will test whether once-monthly MBX-4291 can pair obesity efficacy comparable with approved agents with better gastrointestinal tolerability. JPMorgan sees monthly dosing and tolerability as the core differentiation, but the update remains an early clinical readout where placebo response, safety and durability can reset the product profile. Peers: LLY NVO GPCR AMGN
3
316
$NVO $LLY I constructed some reference profiles for various glp-1s where there's enough published data so they could be used as benchmarks instead of having to look at 6 different trials for the same drug that all have different designs. Mostly adjusts for sex ratio and sponsor reporting bias, and reporting drift over time (novo trial AE rates have drifted down over time for the same drug, and Lilly rates have drifted up). Novo weight loss rates tend to run 5% high compared to others even after adjusting for sex, but that mostly disappears after adjusting for placebo. I looked at BMI enough that I don't think it really makes a difference and left it out. Country matters for AE reporting but not weight loss.
Adjusted to a 65% female population


1
3
926
$NVO I was scratching my head over how 2/3 can be earlier responders then I realized early responder is just an arbitrary threshold they made up. "We aced the test that we wrote ourselves!"

#PRESS Novo’s CagriSema analyses show 67.8% of people studied are early responders, achieving ≥5% weight loss by week 8. Adults with overweight or obesity also reported meaningful quality of life improvements in physical function. Learn more in the press release here: novonordisk.com/content/nnco…

2
5
1,027
So $NVO needs to publish the head-to-head vs tzp were they underperformed by January 9th (1 year after completion). These clinicians don't follow biotech updates (fair enough they're busy working) and they treat publications as if they are new news. So they'll be reminding prescribers that their brand new drug is inferior right as they 're trying to introduce it and get them to prescribe it 😂
2
13
3,194
$NVO hasn't published the head-to-heads they've run of cagrisema vs tzp yet but we can use 2.4 mg and 1 mg sema as common comparators in obesity and t2d respectively. The anchored comparisons are consistent with cagrisema looking better when novo runs it along but underperforming (in both t2d and simple obesity) in head to heads.


