

CMO Los Angeles General Medical Center, hospitalist, infectious diseases expert, researcher
Joined March 2016
- Tweets16.8K
- Following162
- Followers26.6K
- Likes25.6K






Pinned Tweet
Updated Shorter Is Better tables! @absteward found a 2 wk vs. 12 wk 2-stage PJI RCT. Also @rachelpbaden identified a duplication in the CAP trials, so there are now 14 RCTs for CAP, not 15. Updated refs at
bradspellberg.com/shorter-is…


Brad Spellberg retweeted

We couldn't be happier to welcome our new Toemigo to the Toe and Flow team: Robin Tsai, our former resident and fellow, will be Chief of the Podiatry Service, @LAGeneralMed working to #ActAgainstAmputation Thanks to all of the folks who made this happen. – at East Los Angeles, CA


Brad Spellberg retweeted

And this is a huge concern for me, because it seems that for medico legal reasons, if you use AI in medicine, thet are going to refer to the published guidelines as the word of the God's. And this is very dangerous because it might exponentially promote some of the inaccuracies of our guidelines but we the trust that it came from an AI #IDTWITTER
Brad Spellberg retweeted

we need to lean into the "humility of uncertainty", per the wise @BradSpellberg
I'm a generalist and care for patients illnesses that span all organs and systems. I appraise evidence for a living. Most guideline recs are not supported by good evidence, and its not even close. Our best field is cardiology, and still half of recs are just opinions at the end of the day
Hepatology is a field without strong evidence where much of what we do is conjecture (of course with good intentions; they mostly always are)
We need fewer guideline recs, which does not mean you can't discuss pros/cons of different approaches. but we should not be setting the de facto standard of care when the history of medicine has shown time and time again we have erred with this approach

A new @AmCollegeGastro guideline outlines 18 preventive care recommendations for cirrhosis, covering carvedilol, HCC surveillance, vaccines, and more. Only one is supported by moderate-certainty evidence. Lead author @ebtapper discusses the challenges.
ow.ly/tAUI5103mFL

Brad Spellberg retweeted
#IDTWITTER 68M with Pseudomonas aeruginosa bacteremia and septic shock from an obstructing ureteral stone.
Urgent stent placed; stone remains. No renal abscess. Off pressors, clinically improving.
How long treat?
@ABsteward @PaulSaxMD @BradSpellberg @DrToddLee @IDstewardship
52%7 days
11%8–10 days
22%11–14 days
15%«14 days»
336 votes • Final results Brad Spellberg retweeted

I agree with Dr Spellberg
IV lead is a myth #IDXposts
Brad Spellberg retweeted
🫁 Pulmonary MAC/ID folks: #IDTWITTER
We keep teaching that rifampin is needed to “protect” azithromycin from resistance.
But is that actually proven?
For macrolide-susceptible NONCAVITARY MAC, does adding RIF to AZM + EMB prevent acquired macrolide resistance?
10%Yes, I think it does
27%Likely, but unproven
29%No, EMB likely enough
34%We need better data
110 votes • Final results Brad Spellberg retweeted
An 85-year-old has symptomatic, macrolide-susceptible, noncavitary pulmonary MAC.
What is the SINGLE most important factor in your decision to offer treatment versus observation?
#IDtwitter @BradSpellberg @DrToddLee @ABsteward @dralicehan @PaulSaxMD @DousaKhalid
18%Frailty/functional status
1%Estimated life expectancy
20%MAC severity/progression
61%Patient goals/preference
71 votes • Final resultsI like numbers. This discussion done in detail in WikiGuidelines on IE. From 2 papers (Fowler '03 Arch Int Med; Ostergaard '22 OFID), pre-test prob of IE with S. aureus in blood is 1 in 8 (12.5%). Higher if community onset. Lower if line-associated. Higher if more bottles +.

I am not always 100 percent consistent. Community onset with no obvious source most of the time I'm treating 4 weeks...like @BradSpellberg said, if it's 1 bottle and neg TTE yeah...but I vary sometimes based on VBM (vibes based medicine)
and decide overall what your pre-echo prob is. -TTE if it's well visualized study has -LR of 0.3. Meaning, if youre pre-test prob is anything over 6%, your post prob is going to be >2%, and you need a TEE to exclude IE. Unless...
Brad Spellberg retweeted
@DrToddLee @BradSpellberg @syctong @PaulSaxMD @ASPphysician @dralicehan @Josh_S_Davis @IDPharmacometrx @IDstewardship @ABsteward @DrNeilStone @CarlosdelRio7 @IDSAInfo @ESCMID @CIDJournal @SIDPharm #IDTWITTER
12%A
50%B
7%C
31%D
72 votes • Final resultsShout out to my friend Dr. Henry Anyimadu, for his new book about the AMR crisis, Beyond the Cure. I was honored to write the forward. His closing charge: Use antibiotics like a shared inheritance: only when needed, and always with care. Check it out!
amazon.com/dp/B0GR5S39WL/ref…

Brad Spellberg retweeted
I'm going to go with"the data" I'm following the evidence based practice not the "eminent experts".

Brad Spellberg retweeted
The central issue is not whether cefiderocol works. It is whether the certainty implied by a recommendation is proportional to the quality of its supporting evidence. This is why I like so much Wikiguidelines because acknowled uncertainty in a humble way, not from an Ivory Tower

Brad Spellberg retweeted

Real cherry-picking citing a Chinese study but not the meta-analysis by Karakonstantis (quoted only for non-fermenters) finding high rate of Cef-non susceptibility among NDM-CRE (I can confirm it from an Italian viewpoint)
pubmed.ncbi.nlm.nih.gov/3766…

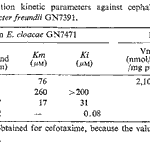
Special shout out to @laocarinadetapi, who has helped me understand this table, which may be key to understanding the entire controversy. He has explained to me that yes, Vmax higher for cefepime means that cefepime is absolutely hydrolyzed by AmpC, even faster than others. But..


The Vmax occurs at the Km (i.e., when the enzyme is saturated by the concentration of the substrate). The key here is that Cefepime's Km is 150 micromolar, but its concentration in the periplasm at the MIC concentration is only 250 NANOmolar (700-fold below the Km.
As such, cefepime is much less hydrolyzed than other cephalosporins because the Km is much higher than the actual periplasmic concentration. So there just isn't much substrate inside the enzyme to get hydrolyzed. Thank you @laocarinadetapi. for clarifying this confusing topic!