

Canada Research Chair in Cardiovascular Disease Epidemiology and Outcomes Tweets/opinions are my own & are not medical advice.
Toronto, Ontario
Joined November 2011
- Tweets4K
- Following1.8K
- Followers1.7K
- Likes12.1K









Husam Abdel-Qadir retweeted

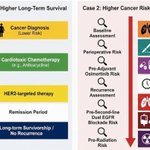
Our #JACCCardioonc review led by @uclaimchiefs @Tylermorad & IM res @MKeykhaeiMD & @A_SteinMerlob tackles the lesser-explored aspects of ICI myocarditis care--the outpatient care, or the aftermath.
🙏 @JACCJournals for the opportunity
#bruinhearts
shorturl.at/PMlfR
🧵1/

Husam Abdel-Qadir retweeted

@CCardiacON spotlight session at #CCS focused on complex valve disease in patients with cancer! Complex cases and great input from interventional cardiologists and cardiac surgeons!


Husam Abdel-Qadir retweeted

🏆 Congratulations to Aman Singh, recipient of the 2026 CCON Best Abstract Award!
The award will be presented at the CCON Spotlight Session during #CCC2026.
#CCON #CardioOncology

Husam Abdel-Qadir retweeted
🫀 CCON at #CCC2026!
📍 Rogers Centre Ottawa | October 15–16, 2026
Join us for our cardio-oncology sessions and AGM! See the full schedule below. 👇
#CCON #CardioOncology
CCON AGM Agenda: bit.ly/CCON-AGM-2026

Husam Abdel-Qadir retweeted

As we get older, some decline in health while others remain robust and active. Dr. Susan Howlett is researching frailty: when health issues layer on top of one another, leaving you vulnerable - specifically, links between frailty and heart failure.
Learn more: bit.ly/4hnacAB.
#HeartandStrokeBeatAsOne

Husam Abdel-Qadir retweeted

Our clinical trial of AMIE, a patient-facing AI system, was just published in The Lancet.
I want to explain what *I* think this study ACTUALLY means.
It's about a fundamental question: how do we know that clinical AI works?
🧵⬇️
xitter.cf/Google/status/21083245…

Our medical research system, AMIE, is the first patient-facing conversational diagnostic tool of its kind to be studied prospectively in a real-world clinical setting.
In a study, published today in @TheLancet, we found that when patients chatted with AMIE before an in-person appointment, the interaction built their confidence and helped them organize their thoughts. And physicians who reviewed the information from the patient conversation got more time back to focus on collaborative care and shared decision-making instead of digging through data.
Husam Abdel-Qadir retweeted

Congrats to our 2026 Young Invesitgator Award winner - Joseph Wallins 🏆
All three researchers did a fantastic job and have contributed greatly to protecting patients hearts.
#GCOS2026 #GCOS26 #GCOS #ICOS #YoungInvestigatorsAward #CancerResearch

Husam Abdel-Qadir retweeted

🫀It's great to have the editors of the #EHJCardioOncology, @dineshpmcc1 @TeresaLpezFdez1 and @AartiAsnaniMD together at #GCOS2026!
We look forward to seeing the research presented at #GCOS develop further and to receiving your best work for publication in EHJ–Cardio-Oncology📖

Husam Abdel-Qadir retweeted

We did not text each other to meet during break. However, during break, we just found and were drawn to each other.
@Dr_Mike_Fradley’s academic children, all working throughout the US. @ICOSociety Sad to not see @sanjaycsekhar. @mealomar @sanathshettydo @snoski14 @USFHealth


Husam Abdel-Qadir retweeted
The Future of Cardio-Oncology is Looking Bright 🤩
Every year at #GCOS, we invite three young researchers to present their work to the broader cardio-oncology community – with the most promising research winning the Young Investigator Award 🏆.
This year's Young Investigators are:
⭐️ Joseph Wallins - "Early dexrazoxane administration is associated with reduced risk of cardiotoxicity in sarcoma patients receiving anthracycline therapy"
⭐️ Mandeep Singh - "Glucagon-Like Peptide 1 Receptor Agonists and Cardiovascular Outcomes in Patients with Type 2 Diabetes Mellitus Receiving Cyclin Dependent Kinase 4/6 Inhibitor Therapy for Metastatic Breast Cancer"
⭐️ Inbar Nardi Agmon - "Upfront Immune Checkpoint Inhibitors and Long-Term Risk of Major Adverse Cardiovascular Events: A Population-Based Propensity-Matched Cohort Study"
Thank you to all three of these researcher for their amazing contributions and presentations. The winners will be announced tomorrow morning.
#GCOS26 #GCOS2026 #Cardiooncology #CardioOnc #CancerTreatment #Oncology #Cardiology #Peptide #Diabetes #ImmuneCheckpointInhibitors #CardioToxicity #Sarcoma


Husam Abdel-Qadir retweeted
#GCOS26 is officially here! 🤩
A full day of global insights and networking starts at 8am sharp. Grab a coffee and get acquainted with the schedule 👇
📰 gcos.ic-os.org/GCOS26Program
#CardioOncology #CardioOnc #WilliamsburgVA


Husam Abdel-Qadir retweeted
#GCOS2026 Cardiooncology programs around the world in collaboration with ESC CO. @TeresaLpezFdez1 @Dr_Mike_Fradley Fantastic and inspiring sessions so far! @husam247 @avirupguha @ICOSociety @CCardiacON

Husam Abdel-Qadir retweeted
Dr. @amyyu_md leads StrokeGoRed, which aims to improve women's stroke outcomes.
With $5 million in funding, innovative approaches, and a team of more than 50 experts across Canada, this team aims to revolutionize women’s outcomes after stroke.
Learn more: bit.ly/4iPXkUV.
#HeartandStrokeScience

Husam Abdel-Qadir retweeted
Submit to #EHJCardioOncology🫀⏭️

Are you working at the intersection of cardiovascular health and cancer care?
The new European Heart Journal - Cardio-Oncology is your journal! Read the advance articles now.
Ready to share your clinical, epidemiological, or translational research with the global ESC community and contribute to the growing evidence base guiding prevention and management of CVD in cancer survivors?
Read the advance articles 👓 ow.ly/ykhc50ZR0cz
Submit your paper here 👉 ow.ly/So4E50ZR0cx
@ESCardioOnco @ESC_Journals #CardioOncology #ESCCardioOnco

Husam Abdel-Qadir retweeted

Today marks 7 years since my stem cell transplant.
I still remember Dr. Thomas Kiss telling me, on this day in 2019, at the Maisonneuve-Rosemont Hospital, “Welcome to your second birthday, because today we are giving you a second life.”
A special thought goes to Jonathan Kehl, the young German man whose stem cell donation gave me this second life.
I was at the Dr. Georges-L.-Dumont UHC today for my monthly immunoglobulin appointment and had a chance to thank nurse Chantal Ferrari as well as the other doctors and nurses that were part of my journey.
Seven years later, I am still as grateful as ever.


Husam Abdel-Qadir retweeted

It might be the most unlikely legacy of 9/11, but 25 years later, the musical “Come From Away” continues to enchant audiences with its story about how Canadians opened their homes to their American neighbors, and the world, in the wake of tragedy.
Husam Abdel-Qadir retweeted

Shana Tova to all my dear Jewish friends, colleagues and neighbours. In this time of immense suffering and loss for many, may the new year bring peace, healing and hope. May our shared humanity always be greater than what divides us. 🕊️#RoshHashanah
Husam Abdel-Qadir retweeted

Lp(a)HORIZON is negative. Does this mean the Lp(a) hypothesis is wrong? I don’t think we can conclude that — at least not yet.
Before seeing the full data, several explanations deserve consideration:
1. Background therapy matters.
In contemporary secondary prevention, aggressive LDL-C/ApoB lowering and comprehensive risk-factor control may substantially reduce the residual risk attributable to Lp(a)
2. Perhaps we are treating too late.
Genetics reflects lifelong exposure to elevated Lp(a). Lowering Lp(a) for a few years after ASCVD is already established may simply be too little, too late
3. Magnitude and duration of Lp(a) lowering may matter.
Not all Lp(a)-lowering strategies are equivalent. We need the achieved absolute levels, sustained reduction, adherence, and exposure over time before extrapolating HORIZON to the entire therapeutic class
4. The benefit may lie in the extreme tail.
Perhaps the clinically modifiable risk is concentrated among patients with very high Lp(a). The prespecified analyses at higher baseline Lp(a) levels will be particularly important
5. Lp(a) concentration may not tell the whole biological story.
OxPL burden, apo(a) isoform size, and particle composition may influence pathogenicity. Two patients with the same Lp(a) concentration may not necessarily carry the same Lp(a)-mediated risk
6. Could the endpoint dilute the signal?
Lp(a) may preferentially affect coronary and recurrent events. Individual MI/revascularization and total-event analyses may tell a different story than first 4-point MACE.
7. Genetics may predict causality better than therapeutic effect size.
Mendelian randomization reflects decades of exposure. It should not automatically be translated into the magnitude of benefit expected from a relatively short pharmacological intervention
8. Are we targeting Lp(a), but not necessarily its most pathogenic cargo?
Lp(a) is the major carrier of oxidized phospholipids (OxPL), which contribute to vascular inflammation, plaque vulnerability and thrombogenicity. Lp(a) concentration may therefore be an imperfect surrogate for its biological activity. The relationship between Lp(a) lowering, OxPL reduction and clinical benefit deserves particular attention
9. Could intensive antiplatelet therapy attenuate the atherothrombotic component of Lp(a) risk?
Lp(a) may promote thrombosis through platelet activation, coagulation and formation of more lysis-resistant clots. OxPL can also interact with platelet receptors. In a secondary-prevention population such as HORIZON, where aspirin and other antiplatelet therapies are extensively used, part of this pathway may already be pharmacologically suppressed — potentially leaving less Lp(a)-mediated risk for pelacarsen to modify
10. Low event rates may be part of the answer.
Despite enrolling 8,323 high-risk secondary-prevention patients, HORIZON required a remarkably long follow-up to accrue the prespecified number of events. This suggests that contemporary secondary prevention substantially reduced the absolute residual risk available for Lp(a) lowering to modify. Nuestro análisis previo ya señalaba que la menor tasa de eventos era una de las principales amenazas para el estudio
11. Was HORIZON powered for a larger effect than the true pharmacological effect?
An event-driven design protects statistical power if the required number of events is reached — but only for the effect size assumed in the design. If short-term pharmacological Lp(a) lowering produces a much smaller benefit than predicted from lifelong genetic exposure, even a trial of >8,000 patients may struggle to demonstrate it
12. The long time required to reach the endpoint may itself be biologically informative.
These were patients with established ASCVD and very high Lp(a), yet events accumulated more slowly than anticipated. Perhaps elevated Lp(a) identifies substantial lifetime risk, but contributes less modifiable short-term residual risk once other major pathways are aggressively treated.
13. Six years is a long time for background therapy to evolve.
During prolonged follow-up, increasing use of PCSK9 inhibitors, ezetimibe, bempedoic acid, inclisiran, SGLT2 inhibitors and GLP-1 receptor agonists — together with improved BP and antithrombotic management — may have progressively reduced event rates in both groups. These potential therapeutic “drop-ins” were already a concern before the results were known
14. First events may not capture the entire Lp(a) burden.
Lp(a) could influence recurrent coronary events and total atherosclerotic burden more strongly than time-to-first MACE. Analyses of total/recurrent events will therefore be particularly important
15. The “risk-factor exhaustion” hypothesis.
With LDL-C around 65 mg/dL, intensive lipid-lowering therapy, antiplatelet treatment, good BP control and contemporary diabetes therapy, multiple atherogenic and thrombotic pathways were already being targeted. HORIZON may therefore have tested Lp(a) lowering in a setting where relatively little modifiable residual risk remained. The published baseline characteristics already showed how intensively treated this population was
16. Perhaps the effect of Lp(a) depends on the surrounding biological environment.
The clinical consequences of Lp(a) may result from the interaction of apoB particle burden + OxPL-mediated inflammation + thrombosis/impaired fibrinolysis. With LDL/ApoB aggressively lowered and most patients receiving antiplatelet therapy, two important components of that environment may already have been attenuated.
Maybe the key question is not simply whether Lp(a) is causal, but WHEN, in WHOM, and HOW MUCH it needs to be lowered to change clinical outcomes.
Until we see the full HORIZON dataset, declaring the Lp(a) hypothesis dead seems premature.
#Lp(a) #LipoproteinA #ASCVD #Cardiology #Atherosclerosis #Horizontes
novartis.com/news/media-rele…

Husam Abdel-Qadir retweeted

📉 Treating high blood pressure is one of the best ways to prevent HF ❤️
✅ Standard control (<140): ~50% less HF
🚀 Intensive/SPRINT (<120): adds ~38% more
💥 Combined: ~69% ↓
🇺🇸 Nationwide, Rx and going intensive could prevent ~167,000 HF cases/year in eligible adults

Husam Abdel-Qadir retweeted
☝️Atherosclerosis starts earlier than we think
👉New data from the REACT study, published in NEJM, provide a striking picture of silent atherosclerosis across adult life:
1️⃣ 16,808 adults, aged 18–70 years, without known ASCVD.
2️⃣ Multimodal imaging included 3D carotid and femoral ultrasound plus coronary CT angiography.
3️⃣ Silent atherosclerosis was present in 57.1% of participants.
4️⃣ Even at 18–29 years, plaque was already present in 8.7% of men and 6.7% of women.
5️⃣ By age 30–39, prevalence reached 34.6% in men and 21.3% in women.
6️⃣Atherosclerosis appeared 5–10 years earlier in men, while women showed a later but steeper rise in midlife.
7️⃣ In younger adults, disease was usually peripheral and single-territory, especially carotid; with age, plaque burden increased exponentially and disease became increasingly multiterritorial.
8️⃣ ☝️Importantly, CAC = 0 did not exclude coronary plaque: among 30–39-year-olds with coronary atherosclerosis, ~42% of men and ~48% of women had zero coronary calcium
9️⃣ SCORE2 showed major discordance with actual disease burden: high SCORE2 had only 1.9% sensitivity for silent atherosclerosis.
☝️Key message: low short-term cardiovascular risk does not mean absence of atherosclerosis.
👉Risk scores estimate events. Imaging detects disease. REACT reminds us that prevention should begin long before cardiovascular risk becomes “high.”
🔗 nejm.org/doi/full/10.1056/NE…
@society_eas


