
Interventional Cardiologist at @TridentHealthPR. Trained @WeillCornell @MountSinaiNYC @GUMedicine #radialfirst #TAVR Not medical advice. Views my own.
Charleston SC
Joined March 2014
- Tweets3.4K
- Following1K
- Followers1.3K
- Likes22.5K


Pinned Tweet
We will demand that everyone admitted to the hospital has quality measures checked. Their blood pressure will be measured at 4 am! Blood thinners for all! Everyone will starve after midnight!
Will that help the patients, sir?
Patrick M Looser MD retweeted

The Keto CTA study is back on my feed today, and the authors are reiterating that it was retracted at their request.
That’s fine. I’m actually open to the idea that the Cleerly data was flawed.
My much, much larger problem is with the way the science was communicated. As they say, “Trust takes years to build, seconds to break, and forever to repair.”
At launch, the message was “no association of ApoB with plaque” and “most participants showed NO OR MINIMAL progression.” (Pictures below.)
But when the authors requested the retraction, the exact same data was suddenly the problem. Plaque progression was so high and so one directional, that it was said to be statistically implausible.
So what is it? No or minimal progression or progression so consistent and so bad that the data must be flawed?
Second, it’s worth remembering how science is supposed to be communicated. Plaque progression was the PRIMARY OUTCOME cited for the Keto CTA study.
But plaque progression was not reported.
The authors later apologized (which, to their credit, is good!) for not including the number in the graph they provided.
But while putting the number in the figure would have been nice, that is not how you DISCUSS your primary outcome in the DISCUSSION of a paper.
Let’s compare this to how @BradStanfieldMD discussed the primary outcome of his Rapamycin study, a study he put a tremendous amount of reputation behind and, quite literally put a second mortgage on his house to get over the finish line:
“4.1 Principal Findings
This randomised, double-blind, exploratory trial evaluated whether once-weekly sirolimus (rapamycin) 6 mg, timed to avoid peak training windows, could enhance functional adaptations to a 13-week resistance and endurance programme in sedentary older adults.
Contrary to the ‘cycling hypothesis’ derived from preclinical models, we found no evidence of benefit. Instead, sensitivity analyses (complete-case and per-protocol) revealed a statistically significant blunting of functional gains in the sirolimus arm. Specifically, participants taking the drug performed fewer chair-stand repetitions and showed non-significant trends toward reduced walking distance and grip strength compared with placebo. Safety monitoring identified a higher burden of minor AEs and one serious infection (pneumonia) in the treatment arm.”
He was clear. The study did not meet his primary endpoint, and instead, the intervention appeared to have worsened it. That is how science is communicated.
I asked Grok to write the Discussion the Keto CTA should have had for its primary endpoint, had it been written the way Dr Stanfield did. Here is what Grok wrote:
"Discussion
Principal Findings
This prospective, single-arm observational study evaluated whether long-term exposure to elevated LDL-C and ApoB (in the lean-mass hyper-responder phenotype on a ketogenic diet) was associated with progression of noncalcified coronary plaque over one year, as quantified by coronary CT angiography. The pre-specified primary endpoint was change in noncalcified plaque volume (NCPV).
Contrary to the hypothesis that these elevations would not drive measurable plaque progression in this metabolically healthy cohort, we observed a median increase in NCPV of 18.9 mm³ (IQR 9.3–47.0 mm³), corresponding to a 42.8% relative change. The mean change was 31.5 mm³ (SD 31.5 mm³), reflecting substantial inter-individual heterogeneity. Most participants showed an increase in NCPV."
That is how you discuss your primary endpoint. It’s not supposed to be a number on a chart (which was omitted anyway).


We, the authors, retracted the paper, @Drlipid
This was due to the anomalous @Cleerlyhealth dataset they provided us alongside their repeated refusal to quality control check their work.
Study participants have since resubmitted their scans and have gotten results far more in line with the other independent analyses from Heartflow and QAngio.
So yes, understandably, we moved to withdraw the paper leading to its retraction.
(This has been known for over half year now.)
xitter.cf/realDaveFeldman/status…

Patrick M Looser MD retweeted

Time to reconsider “nailing the ostium“. Ostial vs Left Main Crossover Stenting in Isolated Ostial LAD Stenosis @JSCAI jscai.org/article/S2772-9303… @mmamas1973 @SandeepNathanMD @mirvatalasnag @Hragy @aymanka @realarainmd @agtruesdell @sbrugaletta @SVRaoMD @SripalBangalore @SCAI
Patrick M Looser MD retweeted

The death penalty is inadmissible because it is an attack on the inviolability and dignity of the person. The common good can be safeguarded and the requirements of justice can be met without recourse to capital punishment: effective systems of detention have been developed that protect citizens while at the same time do not completely deprive those who are guilty of the possibility of redemption. #NoDeathPenalty
I’d like to see AI hold the hand of a dying patient or tell the family their loved one won’t be coming home for dinner.

Patrick M Looser MD retweeted

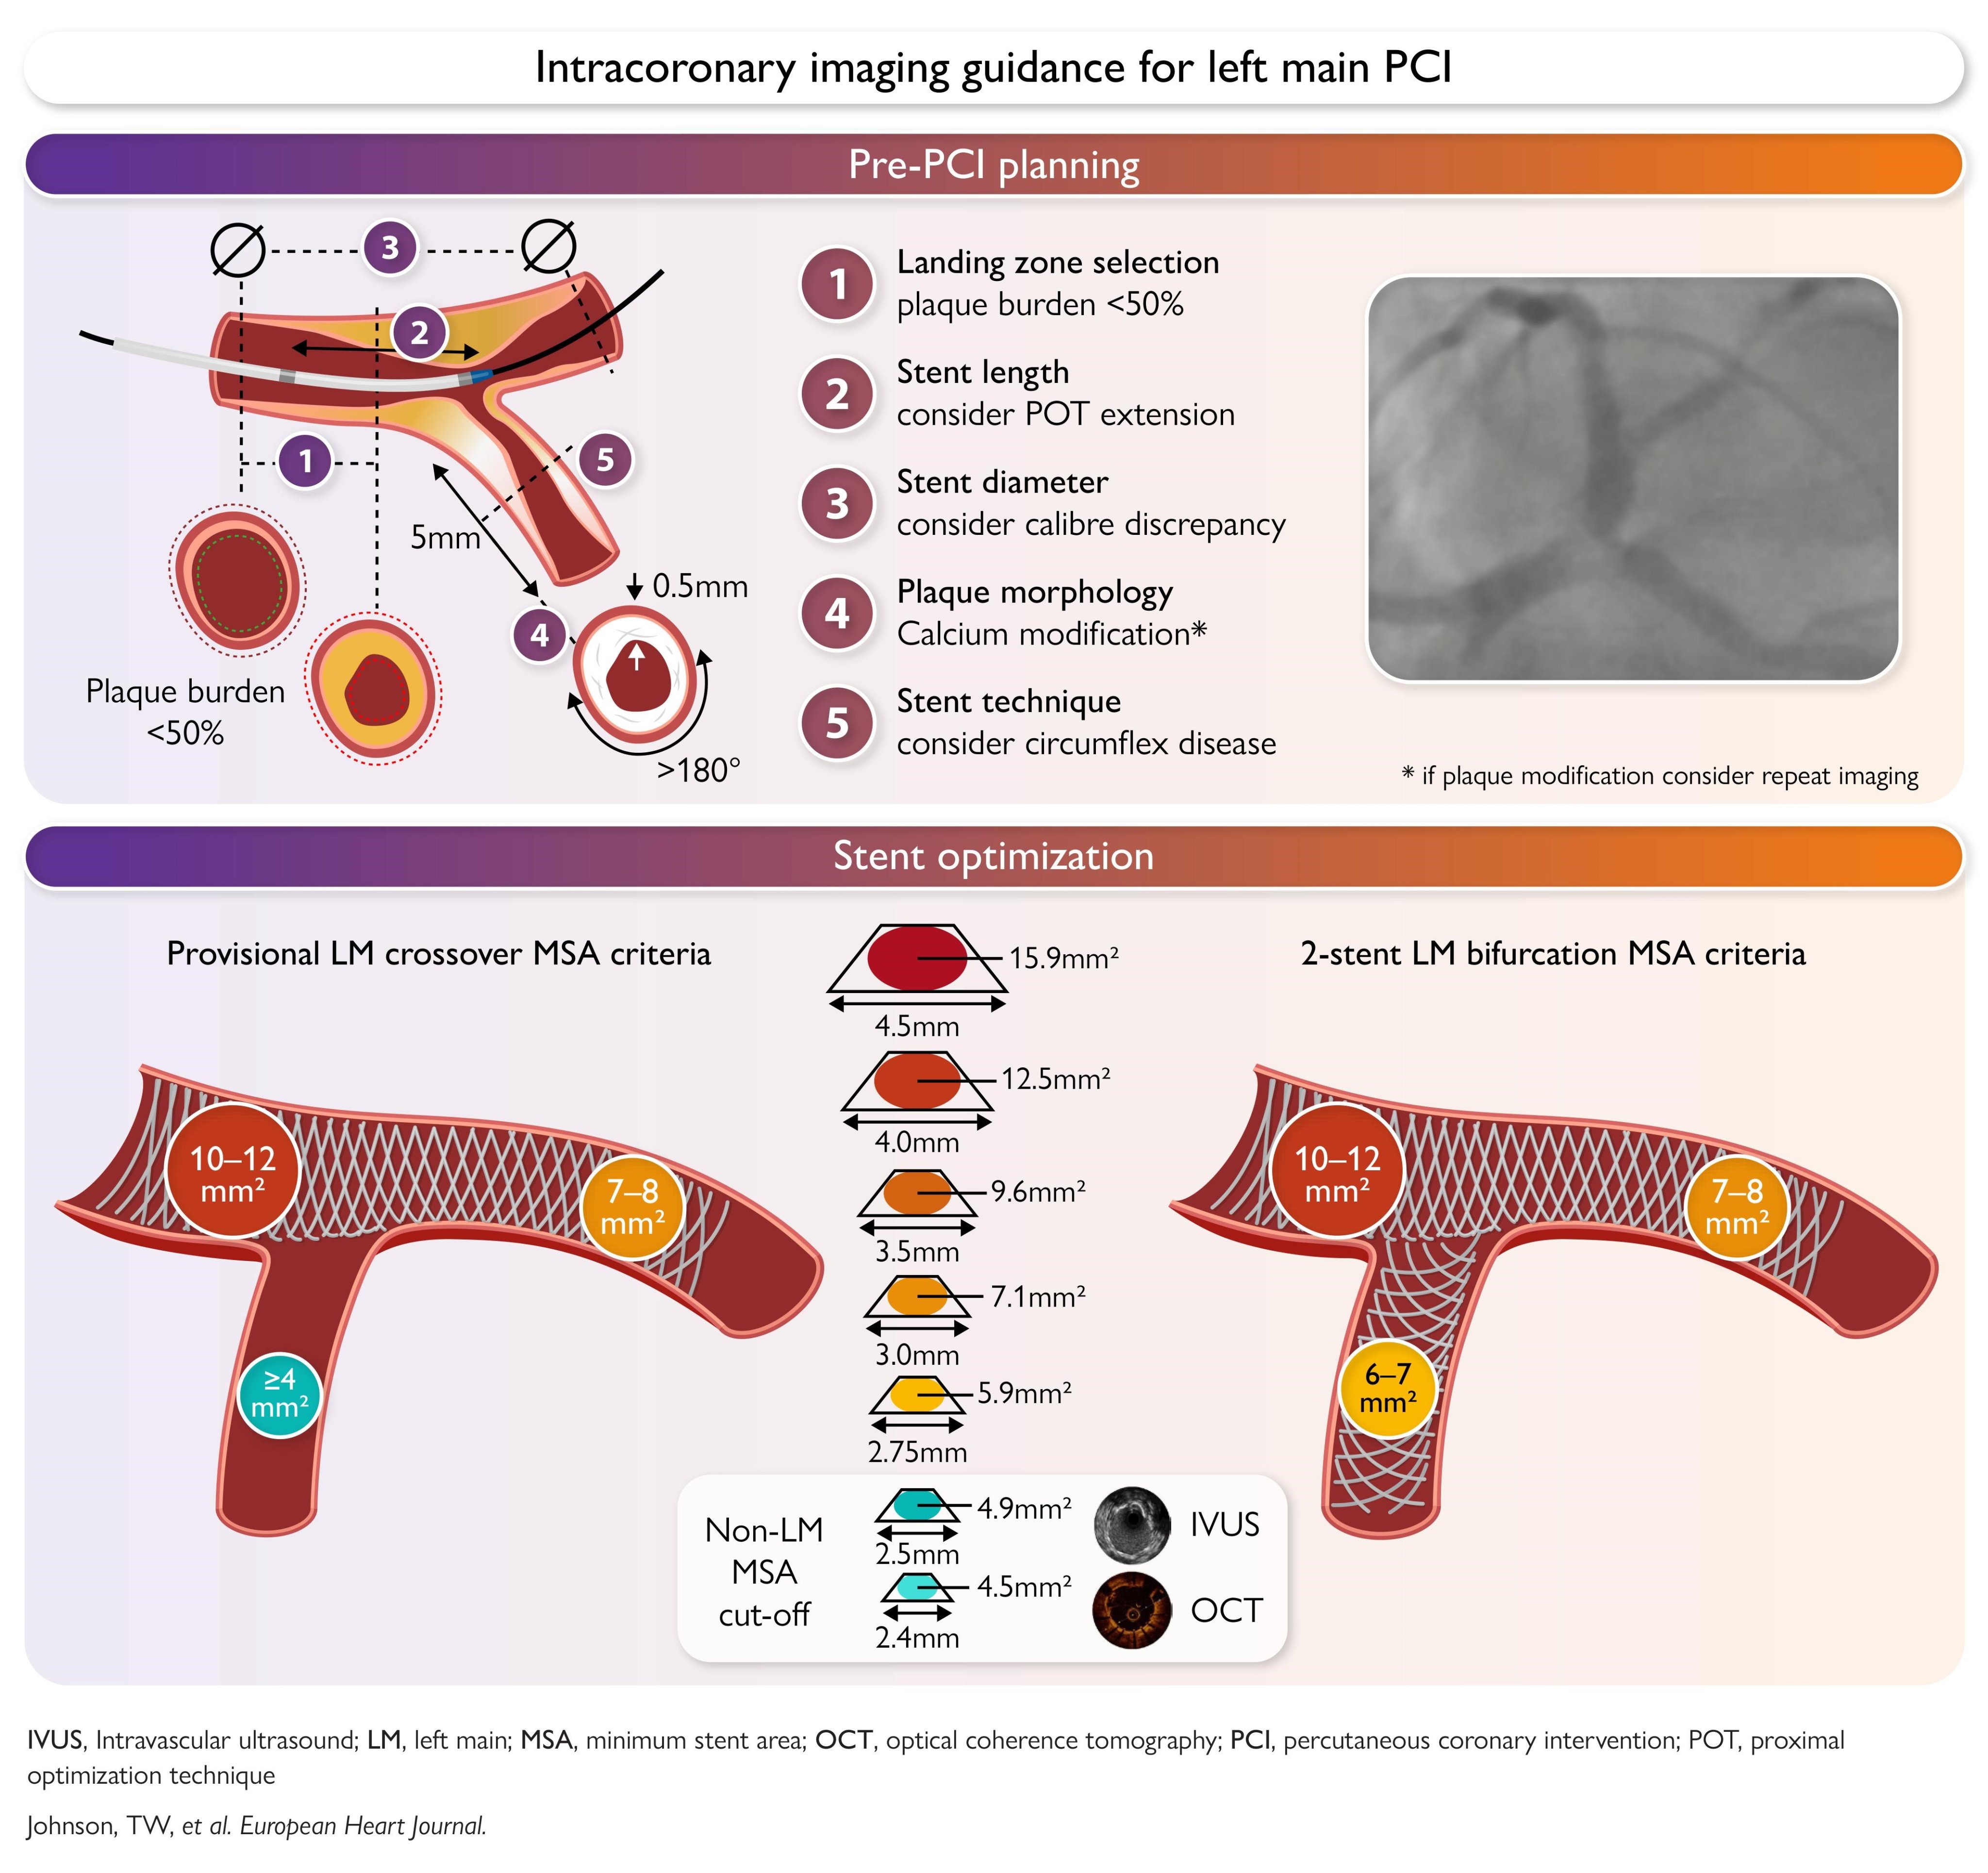
2026 EHJ - Intracoronary imaging for left main percutaneous coronary intervention: a clinical consensus statement of the European Association of Percutaneous Cardiovascular Interventions (EAPCI) of the ESC and the European Bifurcation Club (EBC)
academic.oup.com/eurheartj/a…
Patrick M Looser MD retweeted

New title…entrepreneur and founder. Medicine has changed (for the good…and not so good) and it’s not going to change back. Many docs are looking for ways to augment their lives. Going to use this account to showcase my changing world both in the hospital and out.
Stay Tuned!
Once a week I get a consult for shortness of breath. And once a week I downtitrate or stop a beta blocker and the breathlessness stops.
Patrick M Looser MD retweeted

(l-r) Rod Whiting, @TridentHealthPR; Joe Boykin, Charleston County Council; and @JamesMcbri43743, Charleston City Council at today’s Johns Island Clean Up. We appreciate their support of our soon-to-open @HCAhealthcare Johns Island ER.


Patrick M Looser MD retweeted

#CarotidRevascularization 2026 comprehensive review
Hot off the press & Free for 45 days
We summarized the most important aspects of #CarotidArteryDisease management for your quick review
kwnsfk27.r.eu-west-1.awstrac…
@timir_paul @MichaelMegalyMD @zghouzi @BaylorCardio @BinitaShahMD @SCAI @SripalBangalore @DougDrachmanMD @mirvatalasnag @fjsawaya @kerrigjl @samitshahmd @DrAmirKaki @agtruesdell @Babar_Basir @sanjum @monteleoneMD @sahilparikhmd @ACCinTouch @Pooh_Velagapudi @aayshacader @EricSecemskyMD @KardiologieHH @SVRaoMD @Allison_Dupont @piccoloraf @vascularIR @SDhandMD @AnkurKalraMD @chrisme43177172 @AntoniousAttall @adityadoc1 @djc795 @DrJayMohan @adnanalkhouli @JayMathewsMD @DrLouMDPhD @JGrapsa @cardiojaydoc02 @DLBHATTMD @kmadass @PLooserMD @AaronFrittsMD @DrDamluji @jaygirimd @hvanspall @mmamas1973 @venkmurthy @t_intheleadcoat


Patrick M Looser MD retweeted

My questioning of lipids began in PA school in 2016, when a physician gave our class a lecture on evidence-based medicine. He showed us mortality data on statins. When you look at mortality alone, the number needed to treat can look underwhelming. He also explained relative risk reduction in a way that made it feel, to me at the time, like a Big Pharma manipulation of data.
That lecture planted a seed. I adopted the paradigm that LDL elevation was overblown. More importantly, I convinced myself that I was the exception: lean, fit, insulin-sensitive, weight training, eating “clean,” and therefore somehow protected from the overwhelming evidence linking ApoB-containing particles to cardiovascular disease.
After graduation, I kept studying lipids. In 2019, I became fascinated with arguments built around Eskimo, ancestral, and prehistoric populations. Looking back, I can see how selectively I interpreted that material. I focused on evolutionary narratives and ignored the obvious limitation: many of those populations died young, before modern atherosclerotic disease had decades to develop.
Around the same time, I discovered the Quest Diagnostics Cardio IQ panel. It was still early in its life cycle, and I was excited by advanced lipid testing. I became the primary of a patient who found me at the mom and pop urgent care and somehow knew that I was open to alternative thinking and who wanted to use the same test because, like me, he was lean, fit, and a weightlifter. Neither of us wanted to believe that someone who looked metabolically healthy could still be at risk for myocardial infarction, stroke, or vascular disease.
Then came 2020.
During the pandemic, my questioning of medical authority intensified. I studied the disease as it moved through Asia, then Europe, and by the time it reached the United States, I felt prepared. I worked in urgent care and treated thousands of patients. I wrote to local mayors and sheriffs, pleading with them not to lock us down. I became part of the anti-lockdown resistance, protesting on the streets and am proud of that. That period changed how many of us viewed institutions, public health messaging, and medical authority.
But that skepticism came with a cost.
In 2021, I published a YouTube lecture on the Quest Cardio IQ test. At the time, very few clinicians were talking publicly about these advanced lipid panels. The lecture received thousands of views. In 2022, I found the Labcorp NMR panel and made another lecture. That one also reached thousands of people. I was not just studying this material anymore. I was teaching it.
From 2021 through 2024, I listened to nearly every countercultural medical authority I could find. It started with keto physicians like Gary Fettke and low-carb advocates on social media. Then came the carnivore movement, organ-meat influencers, alternative medicine conferences, and the online war between lipid denialists and lipid-lowering advocates. I even met Shawn Baker at an alternative medicine conference in 2023. The movement reached peak absurdity, in my mind, with the rise and fall of Paul Saladino and Liver King. I learned that they both sourced their supplement line from a manufacturer from a businessman in the supplement industry. I had a decision to make. Do I go full in on this and make millions selling supplements and become such an absurd online personality. I recognized for the first time the meaning of grift. The carnivore influencers had capitalized on a growing health conscious and skeptical market with a “natural” supplement. It was fancied as science perhaps with loose inspiration derived from the anthropological studies of a dentist Weston A Price who found less tooth decay in ancestral populations that at a traditional meat based diet.
I started Iron Direct Primary Care in 2021 as an alternative healthcare home for patients who wanted something outside the conventional system. For years, I cared for many patients who did not believe elevated lipids mattered. We ordered everything: MPO, homocysteine, hs-CRP, omega-3 testing, IL-6, Lp-PLA2, and thousands of NMR panels. Desperately searching for an answer to cardiovascular disease other than LDL and APO B burden.
The pattern was always the same.
Patients had elevated LDL particle number and elevated ApoB, and we often kicked the can down the road. We focused instead on insulin sensitivity, clean diet, seed-oil avoidance, exercise, nitric oxide supplements, methylated vitamins, inflammation markers, and metabolic optimization.
On Instagram, X and podcasts, the lipid battle raged. I listened to lipid skeptics like MD Tro and ex-carnivore MD Paul Saladino, some were compelling. Some were charismatic. Some wore white coats and spoke with absolute confidence. I thought some of them were brilliant. I even referred patients into that ecosystem.
Then reality started to break through.
In 2024 and 2025, I began seeing heart attacks and strokes in my own patient population. That floored me. These were not the stereotypical patients people imagine when they think of cardiovascular risk. These were patients who avoided seed oils, lifted weights, ate clean, took nitric oxide boosters, optimized methylation, and followed the advice of wellness influencers.
Yet they still had events.
There are carnivore FB groups that Carnivorecringe on instagram screenshots and posts revealing a toxic subculture. These self-help groups will gaslight patients who suffer from keto and carnivore with absurd claims like “they weren’t eating enough fats” or “they didn’t give carnivore long enough.”
One patient had a stroke and left my practice to pursue high-priced “natural cardiology” advice form Wolfson for $7,000. Another patient pursued an alternative cardiology path by surgeon Philip Ovadia for also $7,000 and later required triple bypass surgery. These cases forced me to confront something uncomfortable: if I continued to minimize ApoB and LDL particle burden, I might be helping patients feel reassured while their arteries continued accumulating risk.
So I re-read the data.
This time, I looked at the totality of evidence instead of the cherry-picked fragments that confirmed what I wanted to believe. I looked at Mendelian randomization, familial hypercholesterolemia, randomized trials, plaque regression imaging, PCSK9 biology, ezetimibe, statins, and the simple fact that lifetime exposure to ApoB-containing particles is causal in atherosclerosis.
That does not mean inflammation, insulin resistance, blood pressure, smoking, sleep, strength, or diet are irrelevant. They matter. But they do not make ApoB disappear. They do not make LDL particles magically harmless. A lean body and a good fasting insulin do not give the artery immunity from particle exposure.
I have now delisted my older YouTube lectures that were influenced by this lipid-denial ecosystem. I no longer want to contribute to the confusion.
One of the most common patterns I now see online is a medical influencer who has moved away from ordinary patient care, sells supplements, lives in another country (likely to avoid legal consequence) sells expensive diet consults, or gives generalized advice under the protection of “no doctor-patient relationship.” Many of these figures profit from the fear and distrust that exploded during the COVID era. That distrust is real. Some of it was earned. But bad institutional behavior does not make bad science true.
The people most affected by this misinformation are often conservatives. These are my people. They are skeptical of the system, suspicious of pharmaceutical companies, and deeply motivated to take responsibility for their health. I respect that. But skepticism without correction becomes a trap. A recent literature on the political polarization of health outcomes suggests that health and mortality are increasingly diverging along political and ideological lines, favoring better health in liberals.
My mission now is to stop the preventable damage.
I went from lipid denialist to lipid-lowering advocate because my patients, my data, and the broader evidence forced me to change. I still believe in strength training. I still believe in metabolic health. I still believe in nutrition, sleep, sunlight, and personal responsibility. But I no longer believe those things cancel out ApoB.
The new message is simple:
ApoB matters. LDL particle exposure matters. Prevention matters. And changing your mind when the evidence demands it is not weakness. It is clinical maturity.
I was wrong before.
Now I am trying to make it right.
Further readings:
Ference et al., 2017 — “Low-density lipoproteins cause atherosclerotic cardiovascular disease”
This is probably the single best paper for the intellectual foundation of my reversal. It integrates epidemiology, Mendelian randomization, genetic disorders, and randomized trials. The authors conclude that the totality of evidence establishes LDL/ApoB-containing particles as causal in ASCVD, with risk depending heavily on magnitude × duration of exposure.
Read the full open-access paper
Borén et al., 2020 — the mechanistic follow-up EAS consensusThis is the one to read for how atherosclerosis happens: entry, retention, and accumulation of ApoB-containing lipoproteins in the arterial intima and the subsequent inflammatory response. It helps resolve the false choice of “cholesterol versus inflammation” both matter, but ApoB particle retention is upstream in the atherosclerotic process.Read the full open-access paper
Cohen et al., NEJM 2006 — PCSK9 loss-of-function mutationsThis is one of the most persuasive natural experiments. Genetically lower LDL from PCSK9 variants produced dramatically lower coronary disease risk. In one population, roughly a 28% lifelong LDL reduction was associated with an 88% reduction in CHD; in another, a ~15% LDL reduction was associated with ~47% lower risk.Read the NEJM paper
Ference et al., JACC 2012 — lifelong genetically lower LDLExtremely important because it explains why short drug trials can make LDL lowering look unimpressive compared with lifelong exposure. Genetic randomization allows us to ask what happens when LDL is lower beginning early in life.Read the PubMed article and access the full text
CTT Collaboration, Lancet 2010 — 170,000 participants / 26 randomized trialsThis is an excellent paper to revisit for objection about statin statistics. Rather than focusing on one mortality NNT, it looks at outcomes per absolute LDL reduction across a huge randomized dataset.Read the complete paper free on PMC
CTT Collaboration, Lancet 2012 — statins even in lower-risk populationsThis one is particularly relevant to “NNT ≈100” arguments. One important distinction: an NNT around that range can describe major vascular events in relatively low-risk people over a limited follow-up period, but it is not a universal “statin mortality NNT.” Absolute benefit necessarily looks smaller when baseline short-term risk is low.Read the paper / abstract
My original skepticism was not irrational—the mistake was extrapolating a modest short-term absolute benefit in low-risk people into the conclusion that lifetime ApoB exposure was unimportant.
FOURIER — Evolocumab cardiovascular outcomes, NEJM 201727,564 patients with ASCVD. PCSK9 inhibition lowered LDL dramatically and reduced cardiovascular events on top of statin therapy. This is important because it dismantles the argument that the benefit is some peculiar “pleiotropic statin effect.” Different mechanism, same direction: reduce ApoB/LDL exposure → fewer events.Read FOURIER in NEJM
ODYSSEY OUTCOMES — Alirocumab, NEJM 2018Another PCSK9 inhibitor, another randomized trial, another reduction in ischemic events. Primary endpoint: 9.5% versus 11.1% after ACS.And yes. Events were lower in the alirocumab arm. Lipid denialists will say mortality wasn’t reduced enough. But these were patients already managed and in the system able to get emergency care to save from death. Primary composite (CHD death, nonfatal MI, ischemic stroke, or unstable angina hospitalization):903 patients (9.5%) vs 1,052 patients (11.1%).All-cause death:334 patients (3.5%) vs 392 patients (4.1%). That is 149 fewer first primary events and 58 fewer deaths over a median 2.8 years. The relative reduction on the primary endpoint was 15% and met the pre-specified significance threshold.Read ODYSSEY OUTCOMES
IMPROVE-IT — Ezetimibe + statin, NEJM 2015Also philosophically important: lower LDL using a nonstatin mechanism, and cardiovascular outcomes improve further. Again, it is difficult to sustain a hypothesis that the benefit is merely a special property of statins.Read IMPROVE-IT
GLAGOV — Evolocumab and actual coronary plaque regressionThis was one is Anti Aging Medicine. We can reverse plaque? That is regenerative medicine!. LDL reached about 36.6 mg/dL; percent atheroma volume fell, and 64.3% of evolocumab patients demonstrated regression versus 47.3% with placebo.Read GLAGOV in JAMA
PACMAN-AMI — Alirocumab, JAMA 2022This is even more visually compelling because multimodality intracoronary imaging showed not only greater plaque regression but changes consistent with plaque stabilization: reduced lipid burden and thicker fibrous caps. Again, this is Anti Aging and Regenerative Medicine.Read PACMAN-AMI in JAMA
ApoB vs LDL-C discordance — JAMA Cardiology 2024It demonstrates how widely ApoB can vary among people with the same LDL-C or non-HDL-C and quantifies clinically important discordance.Read the JAMA Cardiology paper
There is also a 2025 systematic review of 15 discordance studies involving 593,354 people. ApoB outperformed LDL-C in all 9 studies directly comparing the two in the review. That one is particularly relevant to explaining why I moved away from obsessing over LDL subfractions/NMR toward ApoB. Read the ApoB systematic review on PubMed
And REACT is especially important
The REACT study was just published in NEJM on August 29, 2026. It examined almost 17,000 ostensibly healthy adults aged 18–70 in Denmark and Spain. Atherosclerosis was already detectable in the 18–29-year-old group—8.7% of men and 6.7% of women—and plaque prevalence and volume climbed dramatically with age.
Read the new REACT paper in NEJM
“I am young, lean and fit, therefore these lipid numbers probably do not apply to me.” REACT shows why that reasoning is dangerous: subclinical disease can already exist decades before the person looks or feels like a cardiovascular patient.
The conservative-vs-liberal mortality paper
Elder & O’Brian, Nature Human Behaviour, May 14, 2026 — “The political polarization of health outcomes in the USA.” They found that conservatives in their cohort experienced worsening health during the 2010s and higher mortality in the early 2020s, particularly from internal causes such as heart disease, cancer, and stroke.
Read the full Nature Human Behaviour article
The authors found a mortality divergence associated with political identity; they also found that changing socioeconomic composition of the coalitions, including education, income, and insurance, explained part of the difference

Patrick M Looser MD retweeted

What happens to an unprotected left main that nobody revascularizes?
Western Denmark Heart Registry, 4,848 patients with isolated LM disease, 2002 to 2021, four paths: PCI, CABG, defer at 50% or less, defer above 50% (Catheter Cardiovasc Interv).

Patrick M Looser MD retweeted

I recently performed a #SurgicalStentectomy together with @FaisalBakaeen.
These operations are challenging and full of technical nuances. The decision to remove a coronary stent is never simple and requires careful consideration of anatomy, stent location, distal targets, and the safest strategy for complete revascularization.
A fascinating operation—and a great example of how complex coronary surgery continues to evolve.
#CABG #CoronarySurgery #CardiacSurgery #SurgicalInnovation
To all of the #medtwitter people typing c/f and d/t, what are you doing with all of your free time?
Patrick M Looser MD retweeted

Happy to inform you all that the 2 cases which I did in the cath lab were accepted for presentation in “Best Coronary Exotica” in the TCT Meeting in San Diego California. Two very complex cases of coronary arteriovenous fistulas arising from sinus node branch of right coronary artery were device closed without surgery in cath lab. Unfortunately my multientry 10 year US visa is past expiry date and I am not keen for a long haul travel due to severe backache also. So I asked SR doing Bond after passing DM(in the vacancy of assistant professor) Dr HariKishore Udhayan from Thanjavur who assisted me throughout the case to apply for the US visa and go to US and present it on my behalf. At his age it will be a big thing for him to cherish for lifetime. As an HOD it is my pleasure to see that my juniors are uplifted to much more heights than me. Hope the esteemed US embassy will consider his application to just go there and present it and comeback.

Patrick M Looser MD retweeted

🫀🔬 "Seeing is believing"… but by how much?
9 RCTs of CAC/CTA-guided prevention:
Showing patients their plaque nudges statin/antiplatelet use up ~10 pp and trims LDL only by fractions of an mmol/L
Modest moves
And so far, no ⬇️ in hard CV events in RCTs
👀➡️🤷

Patrick M Looser MD retweeted

My mate back in England married his first ever girlfriend.
They met at school. Never left our hometown. He still works at British Gas, the same company he joined at 21. Heads down the pub every Friday.
They've got two kids, a garden, a dog. She still looks at him like he's the only man in the room.
He's never read Atomic Habits. Never "worked on himself." Never bothered to optimize his supplement stack.
I moved to four countries, built a business, reinvented my entire life. I wouldn't change any of it.
But when he sends a photo of his family eating Sunday roast together, I think maybe we're all overcomplicating this.
Patrick M Looser MD retweeted

Colleague was doing a thoracic spine decompression surgery in a medically sick patient. High risk for paralysis or infection.
Nurse enters the room, uninvited, and starts documenting who has uncovered facial hair on her “facial hair noncompliance” clipboard.
Meanwhile, according to open evidence: Operating room traffic (people entering and exiting) has substantially more supporting evidence than uncovered facial hair as a driver of intraoperative surgical site infection (SSI).
That nurse won’t be the one answering to family or facing a lawsuit in case of a complication. Yet she will smugly write up any personnel who fail to comply with her completely arbitrary rules.

Patrick M Looser MD retweeted

70s male w CABG yrs ago p/w CCS3 angina. Abnormal Nuke >15% TPD. EF 45-50% euvolemic. SVGs to LCX/Ramus/Diag occluded. LIMA patent. Now he’s got severely calcified LM/Ramus/LCX disease. How do you treat? Double Barrel it? 🤣
@nyalborgesmd @mmamas1973 @realarainmd @LAzzaliniMD @agtruesdell @TWilsonMD @SripalBangalore @Obisht @nadig_cardio @DrSiyabMD @aspergian1 @Hragy @mirvatalasnag @jedicath @kalazizimd @PLooserMD @SVRaoMD @DocSavageTJU @Coronary4front @_radikalek
Patrick M Looser MD retweeted

Hi all,
The Lp(a) HORIZON trial has released topline data and, quite shockingly, missed its primary endpoint.
In other words, lowering Lp(a) in patients with prior MI, stroke or peripheral arterial disease, who were otherwise very well treated for LDL-C, blood pressure, diabetes and other risk factors, did not reduce the primary cardiovascular endpoint.
We obviously need to see the full data before making firm conclusions, and I don’t want to speculate too much without the details.
But this is a big enough result that it is worth summarizing what we know, what we don’t know, and what this may mean for our patients after 20+ years of trying to test the “Lp(a) hypothesis.”
What we know:
1-There are hundreds if not thousands of genetic, epidemiologic and Mendelian-randomization studies showing that elevated Lp(a) is associated with MI, stroke, peripheral arterial disease and aortic stenosis. That body of evidence is very strong.
2-However, much of those data come from community-based populations, often before the era of intensive LDL-C lowering and modern secondary prevention.
3-There has been much less information about how much residual risk Lp(a) carries in someone who has already had an event and is then treated very aggressively.
4-HORIZON may have had some of the best-treated patients of any recent cardiovascular outcomes trial.
Baseline LDL-C was about 65 mg/dL, a measured LDL-C contains the cholesterol carried on Lp(a), so in reality, 15-20 points lower.
5-In patients with very high Lp(a), if you correct LDL-C for Lp(a)-cholesterol, the actual LDL-C carried by LDL particles may have been closer to 45–50 mg/dL, perhaps even lower in some patients.
6-This raises a very basic question:
Can you still demonstrate a major incremental benefit from lowering another apoB-containing particle when the underlying LDL burden has already been driven this low?
What we don’t know:
1-What was the actual corrected LDL-C in these patients? I think it would be extremely informative to directly measure Lp(a)-C and calculate corrected LDL-C. This may tell us a lot about the biological setting in which pelacarsen was being tested.
2- What was the OxPL status? Our prior work has suggested that much of the pro-inflammatory biology associated with Lp(a) is related to its enrichment in oxidized phospholipids. Did OxPL fall? Did patients with higher OxPL derive more benefit? Was Lp(a) concentration actually identifying the patients with the most pathogenic particles?
3- Did we measure the right component of Lp(a) for trial inclusion? We generally measure molar particle concentration. But is molar concentration itself the main driver of risk, or is it partly a surrogate for what the particle carries? Cholesterol? Triglycerides? Oxidized phospholipids? Other proteins? Could two patients with the same Lp(a) concentration have very different Lp(a)-mediated risk? I think this question deserves much more attention.
3- Were the genetic data telling us exactly what we thought they were telling us? The genetic data are extremely compelling, but genetics reflect lifelong exposure. A clinical trial treats patients late in life, often after decades of arterial injury and after an event has already occurred. Those are not necessarily the same experiment. Could there also be some unrecognized biology linked to the LPA locus that we have not completely accounted for? That possibility should at least be considered.
3- Does very low LDL-C modify the Lp(a) risk relationship? Maybe Lp(a) is particularly important when LDL-C is higher, but its contribution becomes smaller once LDL-C is driven to very low levels. Again, we need the data.
4- Does aspirin or other antiplatelet therapy reduce part of the risk associated with Lp(a)? Lp(a) has potentially important prothrombotic effects. Almost everyone in a trial like HORIZON is receiving contemporary antiplatelet therapy. Could that blunt one component of the risk associated with Lp(a)?
5- Why are these patients still having events? This may be one of the most interesting questions of all. These are patients with LDL-C around 65 mg/dL, and perhaps corrected LDL-C substantially lower, yet cardiovascular events continue to occur. What is driving that residual risk? Inflammation? Thrombosis? Plaque burden that is already too advanced? Other lipoprotein characteristics? Something we are not measuring?
6- Do we need to re-examine some basic assumptions about atherosclerosis? We have spent decades focusing heavily on the quantity of circulating lipoproteins. But perhaps lipoproteins are relatively benign until they undergo biological modification in the artery wall. Oxidation may be one of those key modifications. For some patients, the answer may be to remove more particles from the circulation. For others, perhaps the better approach is to prevent their oxidation or block the downstream biological effects of oxidized lipids. The recent difficulties with anti-inflammatory approaches, including IL-6 inhibition, make these mechanistic questions even more interesting.
7- Was there something specific about pelacarsen, the degree or timing of Lp(a) lowering, advanced disease, trial duration, background therapy or patient selection that mitigated a potential benefit? We simply don’t know yet. That is why the detailed results will be so important.
What does this mean for patients today?
If you have already had an MI, stroke or PAD, the immediate lesson is very clear:
1- Get all of your established risk factors treated aggressively.
2- Get LDL-C/apoB very low.
3- Control blood pressure.
4- Control diabetes.
5- Don’t smoke.
6- Use appropriate antiplatelet and other guideline-directed therapies.
HORIZON shows us what modern secondary prevention should look like.
If you have elevated Lp(a) but have never had an event, the genetic and epidemiologic data still suggest increased lifetime risk.
Until the other 4 outcome trials read out, I would continue to treat every modifiable risk factor aggressively.
We should wait for those trials before drawing broad conclusions about the entire field.
I think the story of Lp(a) therapy is beginning, not ending.
We also need to show tremendous respect and gratitude to the patients who participated in HORIZON and to the investigators and companies that invested enormous resources to actually test the Lp(a) hypothesis, to the ultimate benefit to peole with elevated Lp(a) to best guide how to manage risk.
More to come as we go forward.